



When It’s Not Just an Itch: Recognizing Vulvar...
We are excited to see so many of you join our FMEP courses. Several of...
Comments Off on When It’s Not Just an Itch: Recognizing Vulvar Cancer Early

We are excited to see so many of you join our FMEP courses. Several of you have requested we continue to post more practice SAMPs, so here you go!
SAMP
Eric Johnson is a 44-year-old man who presents to the local emergency department with severe epigastric pain. The pain has started to radiate to his back. He has had nausea and 3 episodes of vomiting. His BMI is 40. He has poorly controlled type 2 diabetes. He has hypothyroidism and hypertension. He is trying to lose weight and was advised by his gym coach to start a “carnivore diet” where he consumes mostly red meat, butter, eggs, and bacon. On examination, he appears uncomfortable. BP is 136/92, HR 86. His abdomen is soft, but tender on palpation in the epigastric area. His cardiovascular and respiratory examinations are unremarkable.
(10 points)
Answer:
Insulin resistance/poorly controlled diabetes
Obesity
Hypothyroidism
High saturated fat dietary intake
Excess caloric intake
Answer:
ABCs
Supportive pancreatitis management (IV fluids, analgesia)
Bowel rest/NPO initially
Elimination of dietary fats
Treat uncontrolled diabetes (consider insulin infusion if hyperglycemic)
Consider plasmapheresis in severe or refractory cases
Monitor triglyceride levels serially
Answer:
Weight loss counselling
Reduce refined carbohydrates
Reduce saturated fat intake
Minimize alcohol use
Fibrate therapy
Statin therapy if ASCVD risk is elevated
High-dose omega-3 fatty acids (e.g., 4 g/day)
Optimize diabetes and thyroid control
Answer: B
Answer: B (Fibrates and apolipoprotein C inhibitors produce the most substantial reductions in triglyceride levels, whereas statins and icosapent ethyl are primarily used to lower atherosclerotic cardiovascular disease risk in patients with hypertriglyceridemia)
Helpful CMAJ Resource:
https://www.cmaj.ca/content/198/16/E622

We are excited to see so many of you join our FMEP courses. Several of...
Comments Off on When It’s Not Just an Itch: Recognizing Vulvar Cancer Early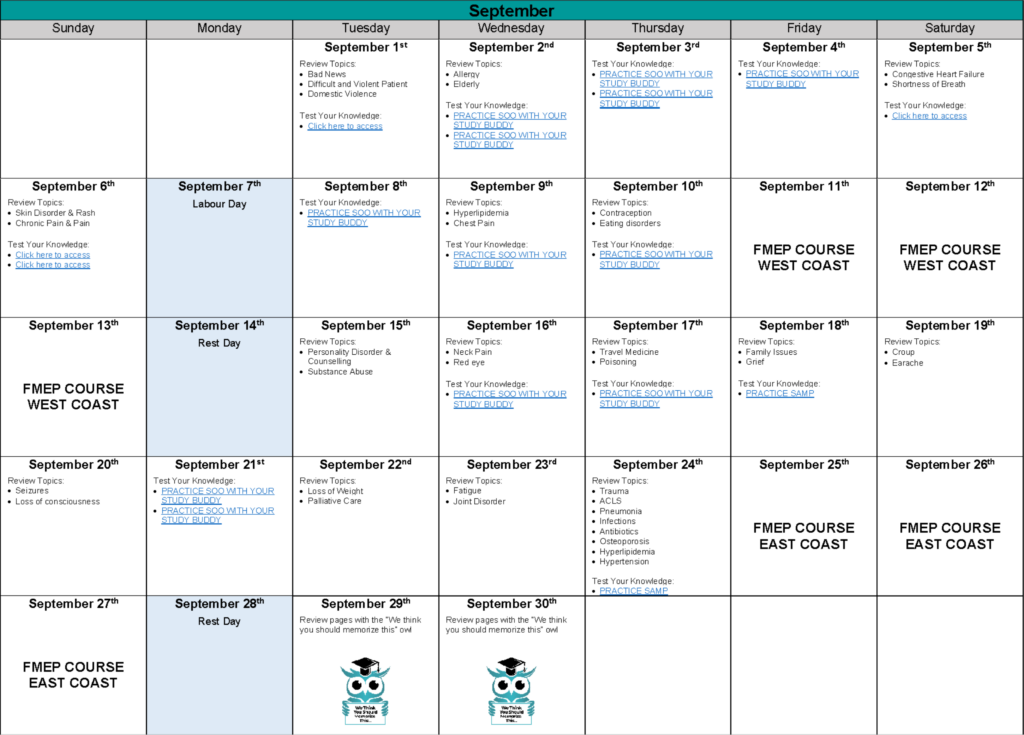
The CCFP exam is quickly approaching, and the FMEP Course is here to help! We...
Comments Off on Put Success on Your Calendar 📅
We are excited to see so many of you join our FMEP courses. Several of...
Comments Off on Burning Feet: Detecting Neuropathy Early
We are excited to see so many of you join our FMEP courses. Several of...
Comments Off on Post-Exposure Protection: Is DoxyPEP Right for This Patient?

